
What Causes Dental Implant Rejection?
Dental implant rejection is a term patients often use to describe implant failure, though true immunologic rejection of titanium implants does not occur in the way the body rejects transplanted organs. Understanding what actually causes implants to fail helps patients appreciate risk factors and take steps to protect their investment. The causes of implant failure fall into distinct categories that patients and clinicians can often identify and address.
Dental implant failure is caused by several factors including failed osseointegration (the implant never bonds to bone), peri-implantitis (progressive bone loss from bacterial infection), mechanical overload, surgical error, systemic health conditions, and lifestyle factors like smoking. True allergic rejection of titanium is extremely rare, affecting less than 1% of patients. The most common causes of failure are preventable through proper patient selection, surgical technique, and long-term maintenance.
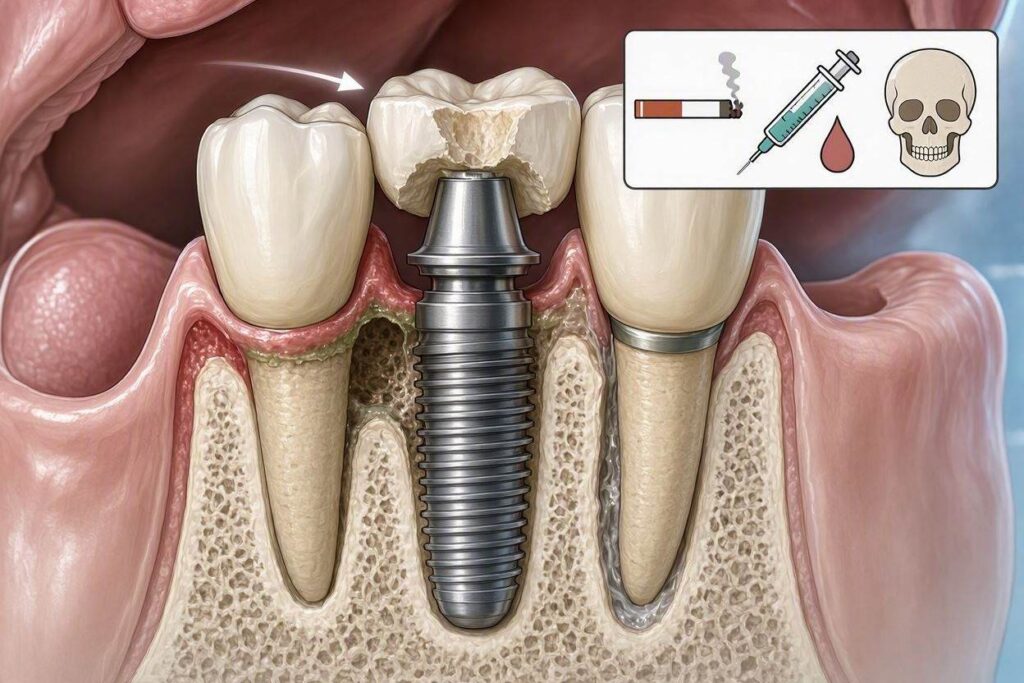
True Implant Rejection vs. Implant Failure
Clarifying terminology helps patients understand what is actually happening when an implant does not succeed.
Titanium Allergy and Hypersensitivity
True allergic rejection would involve the immune system recognizing the implant as foreign and mounting an attack against it. This phenomenon is exceptionally rare with titanium implants.
Why Titanium Is Biocompatible:
Titanium forms a stable oxide layer on its surface that is biologically inert. The body does not recognize titanium oxide as foreign material requiring immune response. Bone cells readily attach to this oxide surface, which is what makes osseointegration possible. Titanium has been used in orthopedic and dental implants for decades with an extraordinary safety record.
Titanium Allergy Reality:
Documented titanium allergy is extremely rare, estimated at less than 0.6% of the population. Most suspected titanium allergies are actually reactions to other metals present in trace amounts within the alloy. Testing for titanium allergy is available but rarely indicated because true allergy is so uncommon.
Symptoms of Actual Titanium Hypersensitivity:
Unexplained implant failure without other identifiable causes. Eczema or rash in some patients with implanted titanium devices. Bone loss without signs of infection. Failure of multiple implants in the same patient despite excellent surgical technique and bone quality.
Patients with confirmed titanium allergy may benefit from zirconia implants, which are metal-free and offer a treatment alternative for this tiny minority of patients.
Why Implants Fail: The Real Reasons
What patients call “rejection” is almost always one of the following conditions.
Failed Osseointegration:
The implant never bonds to bone. Instead of bone growing onto the implant surface, fibrous scar tissue forms between the implant and bone. This is a failure of the healing process, not an immune rejection.
Peri-Implantitis:
Bacterial infection causes progressive bone loss around a previously integrated implant. This is an infectious disease process, not rejection. It is analogous to periodontitis around natural teeth.
Mechanical Overload:
Excessive forces on the implant cause bone loss or component failure. The implant is not being rejected; it is being mechanically damaged.
Failed Osseointegration: Causes and Mechanisms
Osseointegration failure occurs in the early post-operative period before the implant is restored.
Surgical Factors
The surgical procedure itself can compromise osseointegration if not performed correctly.
Bone Overheating:
Drilling into bone generates heat. If the bone temperature exceeds 47 degrees Celsius (117 degrees Fahrenheit) for more than one minute, bone cells die. The implant is then placed into dead bone that cannot heal and integrate. Sharp drills, copious irrigation with sterile saline, and intermittent drilling technique prevent overheating.
Implant Contamination:
The implant surface must remain pristine to achieve osseointegration. Contact with gloves, gauze, saliva, or instruments contaminated with bacteria or chemical residues compromises the surface. Strict sterile technique is essential during implant surgery.
Inadequate Primary Stability:
The implant must be firmly anchored in bone at the time of placement. If the implant moves more than 50-150 micrometers during healing, bone cells cannot attach. Instead, fibroblasts move in and create fibrous encapsulation.
Surgical Trauma:
Excessive pressure during implant insertion, poor incision design, or rough tissue handling increases inflammation and impairs healing.
Patient Factors Affecting Osseointegration
Patient characteristics significantly influence whether osseointegration succeeds.
Bone Quality and Quantity:
Dense, well-vascularized bone heals predictably. Soft, poorly vascularized bone heals less reliably. Adequate bone volume allows placement of appropriately sized implants. Thin or deficient bone compromises implant stability and healing.
Smoking:
Nicotine causes vasoconstriction that reduces blood flow to healing tissues by up to 70%. Carbon monoxide reduces oxygen-carrying capacity of blood. Smokers experience implant failure rates 2-3 times higher than non-smokers.
Uncontrolled Diabetes:
Elevated blood glucose impairs wound healing, reduces immune function, and compromises bone metabolism. Well-controlled diabetes (HbA1c below 7%) does not significantly increase failure risk. Poorly controlled diabetes is a major risk factor.
Medications:
Bisphosphonates and other antiresorptive medications increase the risk of medication-related osteonecrosis of the jaw. Corticosteroids and immunosuppressive drugs impair healing. Some medications affect bone metabolism and healing capacity.
Radiation Therapy:
Radiation to the jaws reduces blood supply and healing capacity. Implant placement in irradiated bone carries higher failure risk, particularly when radiation doses exceeded 50 Gray.
| Risk Factor | Impact on Osseointegration | Management Strategy |
|---|---|---|
| Smoking | 2-3x higher failure rate | Smoking cessation 4+ weeks before surgery |
| Uncontrolled Diabetes | Significantly impaired healing | HbA1c optimization before surgery |
| Poor Bone Quality | Reduced primary stability | Longer healing periods, modified implant selection |
| Medications (Bisphosphonates) | Risk of osteonecrosis | Drug holiday, risk assessment |
| Radiation History | Reduced vascularity | Hyperbaric oxygen, extended healing |
Peri-Implantitis: The Leading Cause of Late Failure
Peri-implantitis is the most common cause of implant failure after successful osseointegration.
How Peri-Implantitis Destroys Bone
The disease process follows a predictable pattern.
Bacterial plaque accumulates around the implant, particularly beneath the gum line. The host mounts an inflammatory response to these bacteria. Inflammatory mediators activate osteoclasts (bone-destroying cells). Bone is progressively resorbed from around the implant. As bone loss advances, the implant loses support. Eventually, bone loss reaches a critical level where the implant becomes mobile or requires removal.
Unlike natural teeth, implants lack a periodontal ligament. The periodontal ligament provides a barrier against bacterial invasion and a source of defensive cells. Without this protective structure, inflammation around implants can progress more rapidly and cause crater-like bone defects.
Risk Factors for Peri-Implantitis
History of Periodontitis:
Patients who have lost teeth to gum disease face the highest risk of peri-implantitis. The same bacterial flora that caused periodontitis colonizes implant surfaces. The same host susceptibility that led to periodontitis operates around implants.
Poor Oral Hygiene:
Inadequate plaque removal allows bacterial accumulation and inflammation. Implant restorations must be meticulously cleaned, just like natural teeth.
Irregular Professional Maintenance:
Patients who skip dental cleanings and checkups miss early detection of peri-implant problems. Professional maintenance is essential for implant longevity.
Smoking:
Smoking increases peri-implantitis risk 2-3 times and reduces treatment response.
Excess Cement:
Subgingival cement remnants from cemented implant crowns cause inflammation and bone loss. Even microscopic cement fragments can trigger significant tissue destruction. This is a leading iatrogenic cause of peri-implantitis.
Poorly Designed Restorations:
Implant crowns with overhanging margins, inaccessible contours, or inadequate emergence profiles trap plaque and resist cleaning. Restoratively driven implant planning and precise fabrication prevent these problems.
| Risk Factor | Relative Risk | Prevention Strategy |
|---|---|---|
| History of Periodontitis | 3-5x higher risk | Treat periodontal disease before implants; enhanced maintenance |
| Smoking | 2-3x higher risk | Smoking cessation |
| Poor Oral Hygiene | Variable, significant | Patient education, regular reinforcement |
| Irregular Maintenance | Variable, significant | 3-6 month recall schedule |
| Excess Cement | Iatrogenic cause | Screw-retained restorations when possible |
| Poor Restoration Design | Variable | Meticulous restorative technique |
Mechanical Causes of Implant Failure
Not all implant failures involve biology. Mechanical factors contribute significantly to implant complications and loss.
Overload and Occlusal Forces
Excessive biting forces damage the implant-bone interface and prosthetic components.
Bruxism (Teeth Grinding):
Patients who grind their teeth generate forces far exceeding normal chewing loads. These forces stress implants beyond their design capacity. Nightguard protection is essential for bruxism patients with implants.
Inadequate Implant Support:
Too few implants supporting a prosthesis concentrate forces excessively. Each additional implant shares the load and reduces stress on individual implants.
Improper Bite Relationships:
Cantilevers (unsupported extensions of a bridge) magnify forces on implants. Poor occlusal design concentrates forces unevenly. Careful treatment planning avoids these problems.
Component Fracture
Mechanical failure of implant components ranges from minor to catastrophic.
Prosthetic Screw Loosening or Fracture:
Screws that attach abutments and crowns to implants can loosen or break under excessive load. Tightening screws to proper torque values and designing restorations for load distribution minimizes these complications.
Abutment Fracture:
The connector between implant and crown can fracture under extreme loads. Zirconia abutments, while aesthetic, are more susceptible to fracture than metal abutments.
Implant Body Fracture:
The implant itself can fracture, though this is rare (less than 1%). Narrow-diameter implants, excessive loading, and material defects contribute to this catastrophic complication.
Systemic and Medical Causes
Certain medical conditions and treatments affect implant success.
Conditions That Impair Healing
Diabetes:
Chronic hyperglycemia impairs wound healing, alters bone metabolism, and reduces resistance to infection. Well-controlled diabetes does not significantly increase implant failure risk, but poor control is a major risk factor.
Osteoporosis:
Reduced bone density may affect implant primary stability and healing. However, osteoporosis is not a contraindication to implant treatment when adequate bone exists. Bisphosphonate medications used to treat osteoporosis present greater concern than the condition itself.
Immunosuppression:
Immunocompromised patients face increased infection risk and impaired healing. Implant treatment may proceed with appropriate precautions and modified expectations.
Autoimmune Conditions:
Conditions like rheumatoid arthritis, lupus, and Sjogren’s syndrome may affect healing and long-term tissue health. Individual evaluation determines implant candidacy.
Medications Affecting Implant Success
Bisphosphonates and Antiresorptives:
Medications for osteoporosis and cancer treatment (Fosamax, Actonel, Boniva, Reclast, Xgeva, Prolia) significantly increase the risk of medication-related osteonecrosis of the jaw following oral surgery. Implant placement in patients taking these medications requires careful risk assessment. A drug holiday may be recommended for certain medications, though this decision must be made with the prescribing physician.
Corticosteroids:
Long-term steroid use impairs wound healing and immune function. Dose, duration, and medical necessity must be evaluated.
Anticoagulants and Antiplatelet Agents:
Blood thinners increase bleeding risk during surgery but do not directly affect implant success. Coordination with the prescribing physician determines appropriate perioperative management.
Selective Serotonin Reuptake Inhibitors (SSRIs):
Some research suggests SSRIs may be associated with increased implant failure risk, possibly through effects on bone metabolism. The evidence is preliminary but warrants consideration in treatment planning.
Genetic and Idiopathic Factors
Some implant failures occur despite excellent surgical technique, good bone quality, and patient compliance. These failures may have genetic or unknown causes.
Genetic Predisposition
Research has identified genetic polymorphisms that may affect implant success. Variations in genes controlling bone metabolism, inflammatory response, and wound healing may predispose certain patients to implant failure. Genetic testing is not currently routine for implant treatment planning.
Cluster Phenomenon
Some patients experience multiple implant failures despite no identifiable risk factors. This “cluster phenomenon” suggests individual susceptibility that current science cannot fully explain. Patients who have experienced one implant failure are at higher risk for subsequent failures.
Preventing Implant Failure
Many implant failures are preventable through appropriate patient selection, meticulous technique, and long-term maintenance.
Patient Selection
Honest evaluation of risk factors before treatment prevents failures. Patients with uncontrolled medical conditions or unrealistic expectations may not be suitable candidates. Patients with significant risk factors may proceed with treatment after understanding modified success expectations.
Surgical Excellence
Proper implant selection, precise surgical technique, and atraumatic tissue handling create the foundation for successful osseointegration. Three-dimensional imaging guides safe, effective implant placement.
Restorative Precision
Well-designed restorations that facilitate hygiene and distribute forces appropriately protect long-term implant health.
Long-Term Maintenance
Regular professional maintenance and excellent home care detect and prevent peri-implant problems before they cause implant loss.
Frequently Asked Questions
Can your body reject a dental implant?
True immunologic rejection of titanium is extremely rare (less than 1%). What patients call rejection is almost always failed osseointegration, peri-implantitis, or mechanical failure.
How do I know if my body is rejecting my implant?
Signs of failing implant include mobility, pain, swelling, bleeding, pus, progressive bone loss on X-rays, and exposure of the implant surface. These indicate failure, not immune rejection.
Can titanium allergy cause implant failure?
Titanium allergy is extremely rare. It may contribute to unexplained implant failures in a tiny minority of patients. Testing is available but rarely indicated.
What is the most common cause of dental implant failure?
Peri-implantitis is the most common cause of late implant failure. Failed osseointegration is the most common cause of early failure.
Can smoking cause implant rejection?
Smoking dramatically increases implant failure risk through impaired healing and increased peri-implantitis risk. It is not immunologic rejection but a failure of biological healing.
Can I be tested for implant rejection before treatment?
No test predicts implant success or failure. Risk assessment based on medical history, examination, and imaging guides treatment planning.
Are zirconia implants safer than titanium regarding rejection?
Zirconia implants offer an alternative for the extremely rare patient with confirmed titanium hypersensitivity. For the vast majority of patients, both materials are safe and biocompatible.
Can a failed implant be replaced successfully?
Yes, in most cases. After addressing the cause of failure, a replacement implant can be placed successfully.
Additional Resources
For more information about dental implant failure causes:
- American Academy of Implant Dentistry: www.aaid.com
- American Academy of Periodontology: www.perio.org
- International Congress of Oral Implantologists: www.icoi.org
- American College of Prosthodontists: www.gotoapro.org



